This article is for educational purposes only. It is not financial advice, not legal advice, and not tax advice. Figures vary by individual circumstances, so consult a qualified professional before acting.
Scenario: You Dual-Apply Two Specialties, Now Your Match Odds Feel Worse
You apply to forty Orthopedic Surgery programs and forty General Surgery programs. In your mind, you just doubled your chances. Eighty total programs. Double the safety net.
That logic is dead wrong.
Dual-applying is not a simple arithmetic addition. It is a dilution of force. When you split your efforts between two distinct specialties, you do not double your odds, you split your narrative signal in half.
Selection committees do not evaluate your application in a vacuum. They evaluate you against candidates who have spent four straight years building a single, focused trajectory toward their field. When a committee sees a dual-applicant, the subtle signs of hesitation stand out immediately. A generic personal statement. Missing specialty-specific electives. Letters of recommendation that lack passionate advocacy. Interview answers that sound rehearsed rather than deeply felt.
The problem is a fundamental mismatch between your primary specialty (your actual goal) and your secondary specialty (your backup plan). Instead of securing a safety net, you end up looking lukewarm to both sides. Lukewarm applicants do not match.
Here is how dual-applying dilutes your application, and the exact protocol to fix it before you submit your application.
What "Primary vs Secondary" Really Means (and Why It Matters)
Let us define the terms clearly.
Your Primary Specialty is your principal professional identity. It is the field where you have directed your rotation energy, built research projects, and established faculty mentorship.
Your Secondary Specialty is your strategic backup. It is typically a less competitive or clinically adjacent field intended to guarantee a match if your primary attempt fails.
Residency selection committees are built to detect commitment. They do not just ask, "Is this person capable?" They ask, "Does this person actually want to be here?"
Commitment Signal = (Depth of Electives + Letter Strength + Story Continuity) / Narrative Contradictions
When a committee reviews your file, they evaluate four core fit signals:
- Depth and contiguity of experiences: Did you actively seek out this field, or did you drop in during the final block of third year?
- Coherence of motivations: Does your personal statement articulate a logical progression toward this specific work?
- Alignment of letter writers: Are the leaders in this field vouching for you as a future colleague?
- Interview consistency: Can you discuss the daily realities of the specialty without slipping into scripts?
If you dual-apply, your application will be compared against candidates who went all-in. If your secondary elements lack proof, or if your primary elements display clear hesitation, committees downgrade your priority on their rank list. You become a risk.
The Dilution Mechanisms: Where Your Application Gets Weaker
Dilution does not happen all at once. It happens across four distinct areas of your application.
1. Narrative Dilution
When you attempt to write two personal statements without a core identity, both statements suffer. You end up relying on vague common denominators like "passion for patient care" or "enjoying procedural skills." These statements lack specific clinical moments that prove you understand the daily work of the field.
2. Portfolio Dilution
Time is zero-sum. A month spent on an elective for your secondary specialty is a month you did not spend doing a Sub-Internship or research project in your primary field. Your ERAS experience entries become a patchwork. Program directors in both fields can see that your clinical exposure is split.
3. Letter Dilution
Faculty members know when you are using them as a backup. If you ask an Internal Medicine attending for a letter to support an Anesthesiology application, or vice versa, the letter will sound hedged. They will write that you are "hardworking and smart," but they will not write that you are "destined to be a leader in this specialty." That distinction moves you from the top third of a rank list to the middle or bottom.
4. Interview Dilution
Interviewing is about authentic communication under pressure. When an interviewer asks, "Why this field?", a single-track applicant answers with spontaneous, concrete experiences. A dual-applicant often stumbles, offering structured but canned answers that lack genuine passion. Interviewers spot this instantly.

Fix #1: Choose Your "Primary Story" First (Even If You Apply Two)
If you must dual-apply, you cannot write two completely unrelated applications. That is a quick path to failure. You must establish a single Master Narrative first.
Your primary story must be built around a simple, non-negotiable rule: Choose the specialty where you can trace an uninterrupted line of evidence from early interest to recent clinical performance.
Do not write two entirely different personal statements from scratch. Use a modular architecture:
- The Foundation Module (40% of statement): Your core medical identity. Why you diagnose, treat, and advocate for patients. This remains identical across both statements.
- The Primary Specialty Module (60% of statement #1): Direct proof of why your primary field is the exact match for your skills and career vision. High-density clinical details.
- The Secondary Specialty Module (60% of statement #2): Framed around shared competencies. Do not frame it as a sudden change of heart. Frame it around the specific overlapping skills (e.g., critical care management, procedural complexity, longitudinal patient relationships) that connect your background directly to this secondary choice.
This structure prevents your secondary application from sounding like a compromise.
Fix #2: Engineer Your Experiences So Primary Looks Deeper and Secondary Looks Intentional
You must hit specific clinical threshold criteria for both tracks. You cannot leave either side empty.
| Metrics & Targets | Primary Specialty Target | Secondary Specialty Target |
|---|---|---|
| Specialty Sub-I / Rotations | 2-3 Advanced Rotations | 1 Structured Elective |
| Faculty Letters of Recommendation | 2-3 Departmental / Sub-I Letters | 1-2 Targeted Field Letters |
| Research / Quality Improvement | 1+ Field-Specific Project | Highlight Shared Skills / Analytics |
| Active Leadership Roles | Specialty Interest Group Lead | Relevant Task Force / Committee |
How to Upgrade "Weak" Secondary Experiences
If you only have two weeks of exposure in your secondary field, do not list it as simple shadowing. Turn it into an active experience entry:
- Passive framing: "Shadowed hospitalists on rounds for two weeks."
- Active framing: "Engaged in daily patient care management, presented clinical cases during multidisator rounds, and analyzed discharge workflow efficiency."
Map every experience to a specific competency. If a program director asks why you spent six months on an Orthopedic research project when applying to Physical Medicine & Rehabilitation, your answer must focus on biomechanics, functional recovery, and musculoskeletal diagnostics. Show intentionality, not accidental diversion.
Fix #3: Letters That Don't Hedge, How to Get Strong Advocacy in Both Tracks
A hedged letter is fatal to your application. If a letter writer says, "This student will make a fine physician in whichever path they choose," the committee knows you are dual-applying.
You must take direct control of your letter request process.
The One-Page Brief Strategy
When requesting letters for either track, supply your writer with a clean, one-page brief. Include:
- Your Primary Thesis: One sentence stating your specific clinical career goal.
- Key Encounters: Two specific patient cases or projects you completed under their direct supervision.
- Target Language: Explicitly ask them to comment on your performance, work ethic, and fitness for the targeted specialty.
Direct Script to Letter Writer: "Dr. Smith, I am applying for residency in [Specialty X]. I thoroughly enjoyed my time on your service, particularly when I managed [Specific Case]. Would you feel comfortable writing a strong letter of recommendation supporting my application to [Specialty X] programs? I have attached a summary brief of my clinical work and goals for your review."
If an attending cannot commit to a strong, field-specific endorsement, thank them for their time and move on to another writer. A generic letter does more harm than a missing one.
Fix #4: Interview & Rank Strategy, Maximize Match Probability Instead of Hope
When interview season arrives, your dual-apply execution shifts to tactical discipline.
Pre-Interview Calibration
Treat every interview invitation as a high-value opportunity. Never tell an interviewer in Specialty B that they are your backup option. Never mention Specialty A during an interview for Specialty B unless explicitly asked about a specific research project or elective on your transcript.
The 3-Part Answer Framework
When asked, "Why this specialty?", use this structure:
- The Core Drive: Identify the fundamental clinical challenge you want to spend your career solving.
- The Concrete Evidence: Reference a specific clinical moment or patient interaction that confirmed this path for you.
- The Immediate Contribution: Explain exactly what skills you bring to their residency program on day one.
The Ranking Strategy
Do not construct a rank list based on fear. Build it using math and clear preferences.
(Note: Conceptual model demonstrating how over-allocating to a secondary specialty weakens overall application signal.)
- Tier 1 (Target/Stretch - Primary Specialty): Rank all primary programs where you interviewed and felt a strong culture and training fit.
- Tier 2 (Safety - Primary Specialty): Rank all remaining primary programs where you received interviews.
- Tier 3 (Target/Safety - Secondary Specialty): Rank secondary specialty programs below your viable primary programs unless you have experienced a clear shift in career preference.
Never rank a program in a secondary specialty above a solid primary specialty program simply out of fear, unless you have genuinely decided that you prefer the secondary career path.
Protocol: A 14-Day Action Plan to Stop Dilution Immediately
If you are currently dual-applying and feel your strategy slipping, execute this two-week recovery protocol.
[Days 1-3: Thesis Lock] ---> [Days 4-7: Briefs & Gaps] ---> [Days 8-10: Drills] ---> [Days 11-14: Ratio Fix]
Days 1-3: Lock the Master Thesis
- Write down your primary specialty thesis in under 30 words.
- Draft your 200-word core foundation paragraph that anchors both of your personal statements.
- Eliminate any statements or phrases in your draft that sound apologetic or uncertain.
Days 4-7: Audit Experiences & Brief Letter Writers
- Audit your ERAS entries. Re-frame every experience using active leadership language focused on core transferable competencies.
- Send one-page briefs to all letter writers. Confirm that your secondary specialty letters clearly endorse you without hedging.
Days 8-10: Execute Interview Drills
- Record yourself answering "Why this specialty?" for both tracks.
- Review the recordings. Check for hesitation, weak explanations, or accidental references to your secondary path.
- Drill your answers until your primary choice sounds seamless and clear.
Days 11-14: Finalize Program Ratios
- Review your target program list. Adjust your application ratio to at least 70% Primary / 30% Secondary.
- Cancel unnecessary secondary applications that do not align with your core goals to save money and mental bandwidth.
When Dual-Apply Is Actually a Strength (and When It's a Trap)
Dual-applying is not inherently wrong. It is simply mismanaged by most applicants.
Go-Ahead Criteria (When it works):
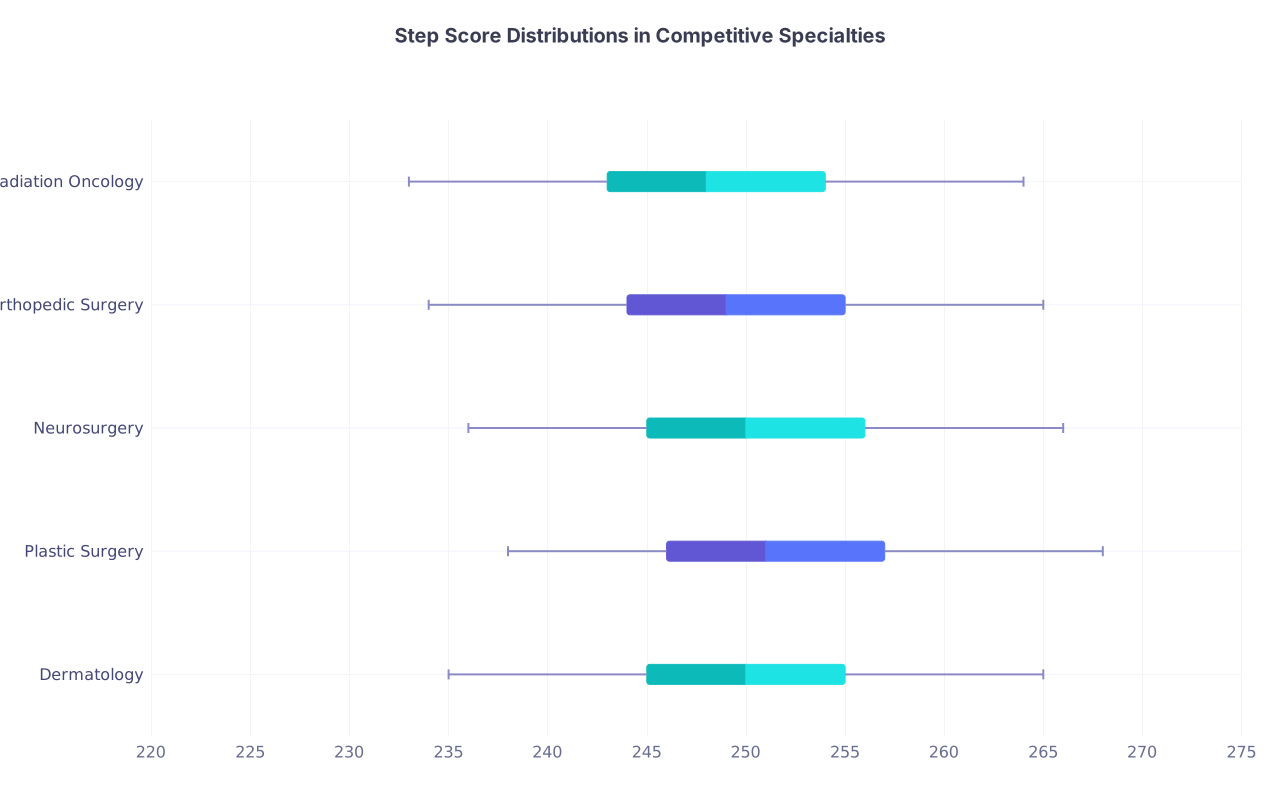
- You are applying to a highly competitive primary specialty (e.g., Plastic Surgery, Dermatology, Orthopedics) and an adjacent, high-alignment secondary field (e.g., General Surgery, Internal Medicine).
- You have solid, verifiable clinical experience in both fields.
- You hold explicit, un-hedged letters of support for both specialty tracks.
Red Flags (When it is a trap):
- You chose your secondary specialty three weeks before the ERAS submission deadline.
- You have zero specialty-specific letters for your secondary track.
- You are applying to two completely unrelated fields (e.g., Radiology and Pediatrics) simply because you cannot make up your mind.
- Your rank list strategy is driven entirely by panic rather than practical career planning.
If you fit the red flag criteria, stop immediately. Strip away the secondary application, focus your resources, and run a clean, targeted campaign on your primary specialty.