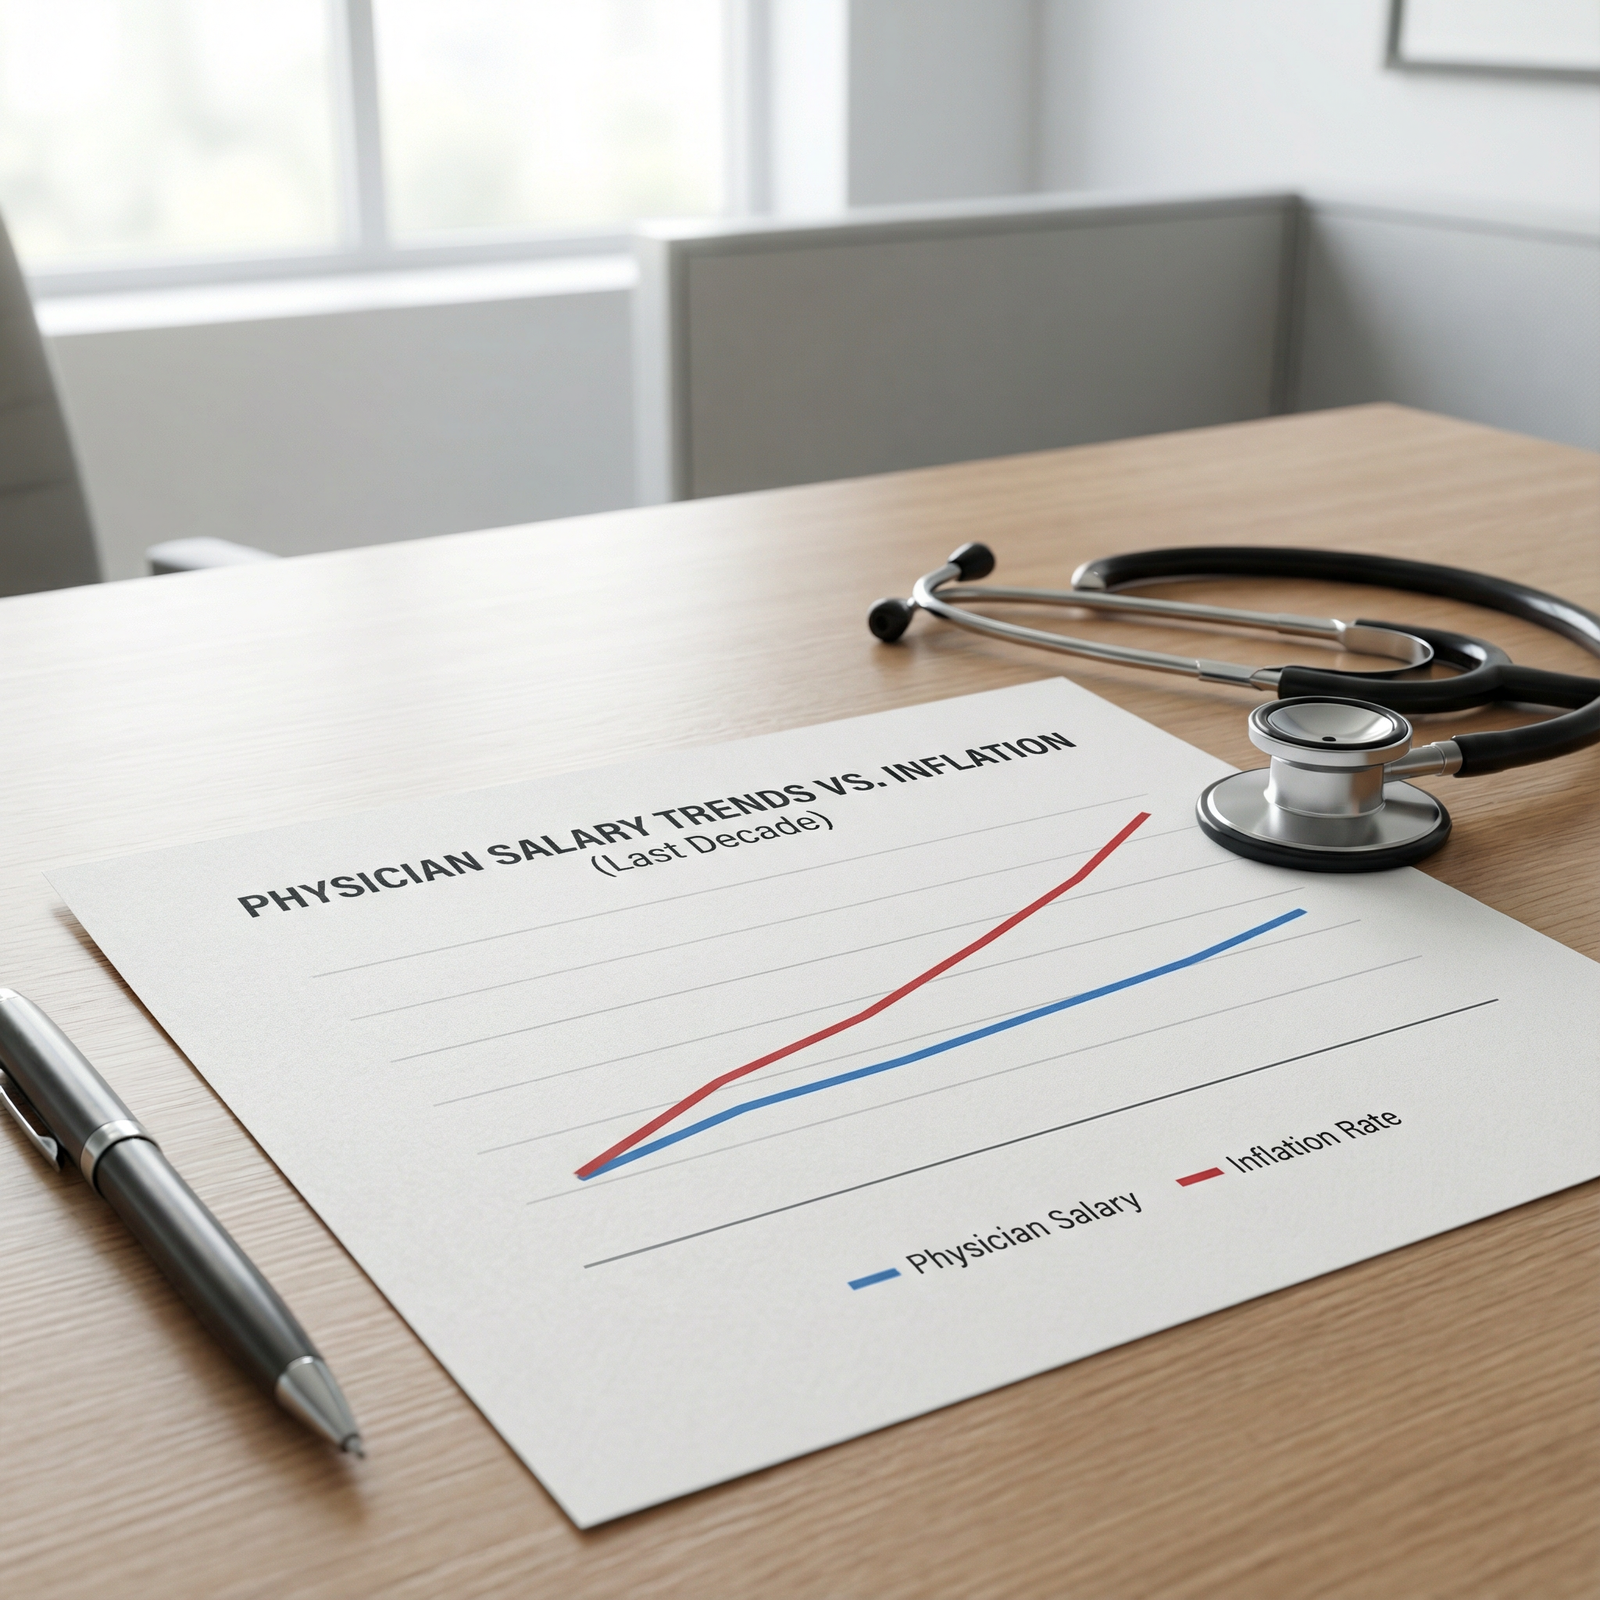
There is a persistent myth in medicine that loyalty is financially rewarded. We are told that putting your head down, doing good work, and staying in one practice for twenty years is the pinnacle of stability. It is a romantic, Boomer-era sentiment. And it is costing you money.
In medicine, "job hopping" carries a stigma. It suggests instability or a difficult personality. Let's redefine the term. Moving every few years isn't instability; it is strategic market recalibration. The reality is that tenure is often inversely correlated with salary growth compared to those who transition every 3-5 years. Your current employer has no incentive to pay you market rate when they can pay you yesterday's rate.
(For deeper insights, learn more about how new hires compare to veterans regarding salary compression.)
This article is intended for educational purposes only. It is not financial advice, not legal advice, and not tax advice. Specific figures vary widely by region, specialty, and contract structure; consult a qualified professional before making career changes.
The Data: Tenure vs. Total Compensation
Let's look at what the data actually shows. Historical compensation surveys from organizations like MGMA and AMGA consistently reveal a uncomfortable truth: physician salaries are rising, but the raises are not evenly distributed. The money follows the movers.
The phenomenon at play is "Salary Compression." Here is how it works: Your base salary was set the day you signed your contract. You get a 2% or 3% annual raise, if you're lucky, while inflation runs hotter. Meanwhile, the market rate for your specialty increases by 5% to 7% annually because health systems are desperate to recruit new talent to fill gaps. Your employer will pay a new hire 15% more than you make right now to do the exact same job, simply because that is what the market demands. They will never offer you that rate to stay.
It is also important to recognize that market cycles in physician hiring can significantly influence whether your move results in a substantial gain.
I call this the "loyalty penalty." By staying in a static employment model, you are effectively taking a 5-10% annual pay cut relative to the market value of your labor. The gap compounds. By year five, you aren't just behind; you are significantly behind, subsidizing the hospital's bottom line with your lost wage potential.
Before finalizing your exit, read our guide on how board certifications affect your compensation to ensure your market value is truly maximized.
The Mechanics of Strategic Transitions
Moving isn't just about resetting your base salary. It is about accessing a suite of financial incentives that are only available to new hires. Internal promotions rarely come with signing bonuses. They don't cover your moving expenses. They don't reset your RVU productivity targets to a favorable baseline. When you switch jobs, you force the market to compete for you again.
When comparing offers, remember to avoid common salary comparison errors by evaluating the full benefits package rather than just the base pay.
You must start treating your salary like a perishable commodity. Perform a "Market Rate Audit" every two years. Look at what competing practices in your region are offering for your exact scope of practice. If the market rate is 10% higher than your current compensation, you have a decision to make.
But moving isn't free. The biggest mistake physicians make is chasing a higher salary without calculating the "Exit Costs." You need to account for unvested retirement match contributions, unused CME stipends, and the dreaded malpractice tail insurance. If your current employer holds your tail hostage, moving to a new job with a $30,000 salary bump might actually cost you $50,000 in uncovered liability. The math has to work.
When Tenure Actually Pays Off
Let's not be dogmatic. Tenure isn't always a financial loser. There are specific scenarios where staying put is the smartest financial move you can make.
The most obvious is the private practice partnership track. If you are on a path to equity ownership in a thriving practice, leaving before you vest is often financial suicide. The value of owning a piece of the machine, profit distributions, building depreciation, and eventual buy-in, almost always outpaces the marginal salary gains of moving to a hospital-employed role. This is the core difference between private practice and corporate medicine. In private practice, you are building an asset. In hospital employment, you are a line item on a budget. You don't build equity in a hospital job.
The second scenario is the "Golden Handcuffs." These are the non-monetary benefits that have real financial value. If you have a leadership role that grants you true schedule autonomy, or a call schedule that lets you actually see your kids, or a culture that protects you from burnout, those things are worth real money. A 15% raise isn't worth it if it puts you in a toxic environment that sends you to an early grave.
I've seen physicians chase a $20,000 raise only to inherit a nightmare call schedule and a restrictive non-compete that trapped them in a geographic dead end. If the cost of leaving is higher than the market rate increase, stay. But be honest with yourself about the math. Don't confuse comfort with financial security.

Conclusion: The ROI of Mobility
The data is clear: the medical market rewards the active, not the idle. If you are in a standard employed role, waiting for your institution to recognize your value is a losing strategy. You have to build your "career capital" so that you aren't dependent on one employer's mercy.
Job hopping isn't a character flaw. It is a financial tool. Use it.