
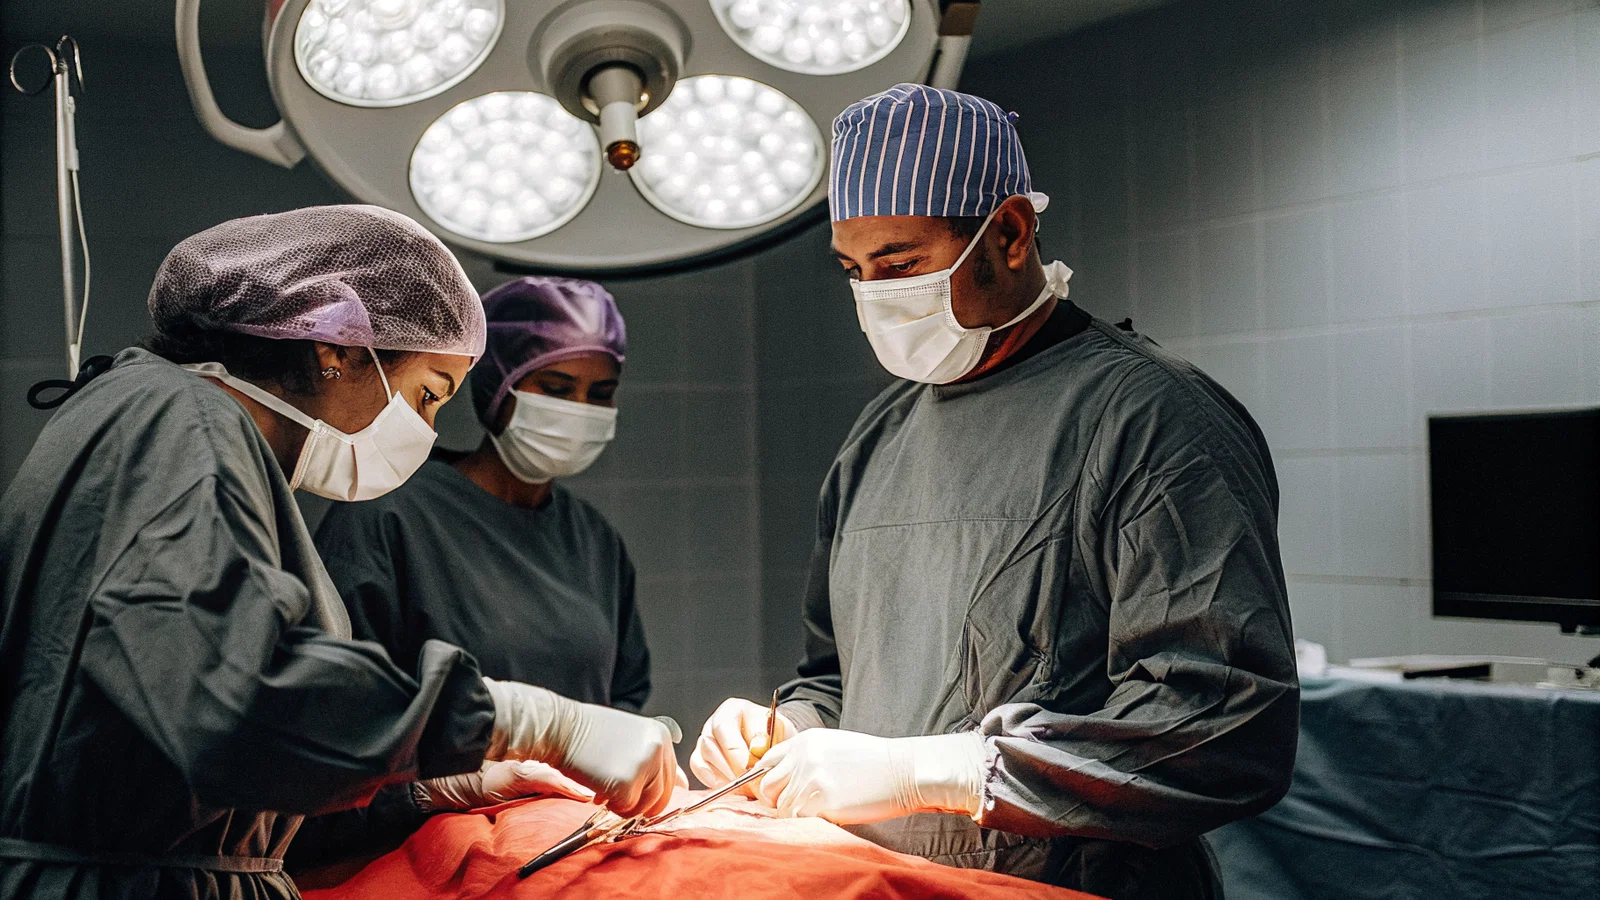
It's 6:45 AM on your first day of internship. You're standing in the OR, gown up, gloves on, staring at a dashboard that lists you as "Observer." Your male co-intern, who had the exact same orientation, is listed as "First Assist." Neither of you requested anything different, the assignment just happened. Multiply that moment by a hundred. By the end of PGY2, you'll have 40 fewer critical cases than he will, and nobody will have said a word about it. That's not a hypothetical. That's what the data shows, year after year, in surgical residencies across the country. I've seen it up close, and I'm tired of pretending it's a fluke.
This timeline is your intervention. It's built on national operative log statistics, bias audit research, and the hard-won wisdom of residents who fought for their numbers, and won. Use it to audit, advocate, and absolutely refuse to graduate with a deficit you never deserved.
This article is for educational purposes only. It is not financial advice, not legal advice, and not tax advice. Figures vary by individual circumstances, so consult a qualified professional before acting.
Orientation Week: Establishing Your Baseline and Audit Protocol
Before you've logged a single case, you need to plant the flag. Most program directors will talk about "supportive environments" during orientation. Nod, smile, then go verify your program's accreditation standards around diversity reporting. Ask for the last three years' anonymized operative logs broken down by gender. If they're suddenly evasive, take note, you'll need to be your own auditor from Day One.
At this point you should secure real-time access to the electronic operative log system, not just the monthly summary, but the moment-by-moment case assignment tool. Know how roles get assigned in your program: is there a chief resident who doles out primary surgeonship? An attending who defaults to the person standing closest? Be the person who asks, "What is our process for ensuring equitable first-assist ratios across residents?" before anyone has a chance to fall into a pattern.
Data from multiple multicenter studies shows cumulative case volume gaps can emerge within the first 90 days if role distribution isn't actively monitored. That gap isn't caused by slower learning or lower confidence; it's caused by systems that let male residents step into primary roles while female residents are subtly steered toward retracting or "helping." By the numbers: female residents historically trail male peers in complex vascular, thoracic, and orthopedic modules by an average of 12%. That's not a gap, it's a crater, and it starts right now.
Your job this week: set up a private tracking spreadsheet. Every week, you'll pull your cases, note your role (primary surgeon vs. first assistant vs. observer), the case's complexity level, and the attending's name. At the same time, quietly compare your ratio to the department's overall distribution. If your ratio of primary to assistant for high-complexity cases dips below 1.0, you escalate. No waiting until the mid-year review. That's too late.
R1 Year: The Critical Window (Months 1-12)
The first 12 months are where the numbers stick. I've watched female residents get complimented for their "teamwork" while their male counterparts rack up 15 primary surgeon cases in the same month. It's not malice; it's default. And default is a career killer.
Months 1-3: Claim Your Knife
At this point you should be negotiating for primary surgeon status on every eligible procedure. Not asking for permission, negotiating. When you're assigned a case, say, "I'll take the lead, with Dr. X supervising." If you're told no, ask for a concrete reason. Is it safety? Fine, what's the specific skill gap, and when will you have the chance to close it? Document that conversation. I've seen too many residents accept "first assistant" labeling on shared cases because it feels polite. Politeness won't get you through your boards.
Avoid the trap of passive observation. If you're standing in the back during a laparoscopic cholecystectomy, you're not learning, you're spectating. Request the camera. Ask to do the port placement. Every small intervention counts, and the logs don't differentiate between "passively present" and "actively engaged." They just count cases. Make every case count toward a skill you actually need.
Month 6: The Mid-Year Chasm
By mid-year, the disparity becomes statistically visible. Comparative data from skills assessments shows a pronounced divergence in laparoscopic manipulation, with male residents averaging 25-30% more hands-on exposure by this point. It's not ability, it's opportunity. If you're behind, don't rationalize it with "I'll catch up during PGY2." The cumulative chart I'm about to show you doesn't bend upward at the end. It fans out.
At this point you should implement a weekly case claim protocol. Every Friday, cross-reference your personal log with the official system. If a case you scrubbed on is missing or your role is downgraded, fix it before the weekend. The system is fallible; people mis-enter roles under pressure. If you let a discrepancy sit, it becomes "your word against theirs." Resolve it while memory is fresh. Send a polite email: "I was listed as first assistant on Case 7821, but I served as primary surgeon for the critical portions, can we correct this?" You'll be surprised how often it works.
Programs with structured, assigned mentorship produce a 25% smaller gender-based volume disparity than those that rely on happenstance. Find your faculty sponsor aggressively, preferably a senior surgeon with institutional clout who will put you on cases and defend your role. If they're not available, buddy with a senior resident who values equity and will hand you the needle driver.
R2-R3: Leadership Accumulation and Strategic Interventions
The middle years are where the gap calcifies, or closes. By now, you've built a reputation for working hard and being "easy to teach." That's dangerous if it translates to "she'll never complain, so put her on the low-acuity service." The data on leadership roles in codes and traumas is stark: female residents are offered the chance to run a resuscitation 30% less frequently than male colleagues with identical ACLS performance scores. I've personally watched an attending say, "Let's let the big guys do compressions" while the equally capable female resident stood waiting. It's not subtle. It's systemic.
PGY2 Onset: Take the Helm
Your focus now shifts from volume to autonomy. Don't get seduced by high numbers that come from repetitive, low-complexity elective clinics. Inflating your total case count with 70 appendixes won't make you a better surgeon; missing 20 complex vascular cases will absolutely hurt you. At this point you should be targeting at least one high-acuity primary case per week, level 1 traumas, open aortic procedures, complex oncologic resections. If your program tries to cluster female residents into breast clinics or thyroid services because they're "more empathetic," push back with the board eligibility requirements. You need a certain number of each category to sit for the exam, and nobody else is going to track that for you.
Conduct a quarterly bias audit using the "First Assist Ratio" metric. That's the ratio of cases where you acted as primary surgeon to cases where you were first assistant, for high-difficulty board-certifiable cases. Your target is under 1.0. If you're assisting more than leading, that's an alarm. Share the data with your program director, not as a complaint, but as a proposed improvement: "Here's my ratio for the past quarter, 0.7 for trauma, 0.6 for vascular. I'd like to bring that to 0.9 next quarter. Can we work on case assignment?" Use the data to empower your requests.
PGY3: Own the Lists
By the final year of core residency, you must have equitable access to the most complex pathology your institution sees. If you're consistently getting the "easy gallbladder" while your male counterpart scrubs the Whipple, something is broken. Aggressive self-advocacy at this stage is not optional; it's survival. Residents who push for case ownership, male or female, show faster competency progression and higher confidence scores in post-training assessments. The data literally supports asking for more.
Run this workflow religiously. The power isn't in any single step, it's in the loop of tracking, documenting, and escalating that makes your expectations impossible to ignore. I've seen programs shift their entire case assignment structure after one resident presented this flowchart and four months of discrepancy data. It works because it's evidence-based, not emotional.
Post-Residency Trajectory: Translating Volume to Career Velocity
You won't fully appreciate the damage of a case volume gap until your first faculty meeting where "research productivity" determines lab space. Longitudinal studies following surgical graduates show that pre-faculty operative volume is the single strongest predictor of grant funding success and promotion speed. A 15% gap in residency translates into a median delay of 2.3 years to associate professor. That's real income lost, not to mention the erosion of leadership opportunities. Closing the gap during training isn't just about fairness; it's a direct investment in your future career trajectory.
Beyond individual metrics, departments with gender parity in case volume report measurably lower burnout rates and more cohesive team dynamics. So your advocacy lifts everyone. When hiring and promotion committees see a portfolio heavy on unique procedural experiences and outcomes, it drowns out implicit bias whispers about "commitment" or "aggressiveness." Compile that portfolio now: a short document listing your top 20 highest-complexity cases as primary surgeon, with any interesting twists, complications managed, or innovative approaches you used. You'll hand it to chairpersons when negotiating your first job contract.
Finally, keep a transparent tracking habit after training, an annual audit of your own case spread, your first-assist ratios, your complex vs. routine mix. Be the attending who notices when junior residents are falling into the same old patterns, and hand them your flowchart. Systemic change happens when we refuse to let the data stay hidden.
Your Action Plan
- Week 1: Audit protocol. Secure log access, pull historical sex-disaggregated data, and set up your personal tracking sheet. Know your baseline.
- Months 1-3: Negotiate or dispute. Demand primary surgeon status on safe, appropriate cases. If denied, document the reason and set a date for reattempt.
- Month 6: Run the numbers. Compare your cumulative primary cases to the national median for your level. If you're below, meet with your faculty mentor and present the gap.
- PGY2-3: Quarterly bias audit. Calculate your First Assist Ratio for high-difficulty cases. Target under 1.0. Escalate discrepancies in writing.
- Post-residency: Build your advocacy portfolio. List your top procedural experiences, and use them to counter biased assumptions. Continue annual personal audits and pay it forward.
The data is infuriating, but it's also liberating. Once you see the pattern, you can break it, for yourself and for everyone coming up behind you. You're not imagining things. The gap is real. And with relentless, organized, data-backed advocacy, you'll close it.




